causaldef
Decision-Theoretic Causal Diagnostics via Experiment Deficiency
Implements a deficiency-theoretic framework for causal inference,
grounded in the classical theory of statistical experiment comparison,
as described in Akdemir (2026)
causaldef

causaldef implements a deficiency-theoretic framework for causal inference, grounded in the classical theory of statistical experiment comparison, providing quantitative bounds on information loss from confounding, selection bias, and distributional shift.
Unlike traditional sensitivity analysis which focuses on “how much bias”
exists, causaldef answers the decision-theoretic question: “how much
regret” might we incur by acting on this evidence?
Key Concept: Deficiency (δ)
The deficiency δ is a theoretical measure of the information gap
between your observational data and a perfect randomized trial. In
practice, causaldef provides a computable proxy $\widehat{\delta}$
based on propensity-score TV balance (PS-TV), which is informative about
overlap/positivity and residual confounding risk.
For bounded utilities with range $M$ (max minus min), the manuscript provides:
- a regret transfer penalty (upper bound term) of $M\cdot \delta$, and
- a minimax safety floor (lower bound) of $(M/2)\cdot \delta$.
policy_regret_bound() reports both quantities.
Scientific Contract
causaldef is theory-forward, but not every exported quantity is the
same kind of object. The package distinguishes:
- Theorem-backed quantities: closed-form or theorem-aligned
utilities such as
policy_regret_bound(),policy_regret_bound_vc(),confounding_frontier(),sharp_lower_bound(), andwasserstein_deficiency_gaussian() - Computable deficiency proxies:
estimate_deficiency()currently returns a PS-TV proxy, not a generic nonparametric estimator of the exact deficiency - Sensitivity diagnostics:
nc_diagnostic()combines an observable residual-association diagnostic with a user-supplied alignment parameterkappa - Experimental heuristics: some specialized modules expose effect estimates together with heuristic proxy scores; those help with exploration, but they should not be read as exact deficiency estimators unless stated explicitly
Installation
You can install the development version of causaldef from GitHub with:
# install.packages("devtools")
devtools::install_github("denizakdemir/causaldef")
Core Features
- Deficiency proxies:
estimate_deficiency()(PS-TV overlap/balance proxy) - Policy regret bounds:
policy_regret_bound()(transfer penalty + minimax floor) - Negative control diagnostics:
nc_diagnostic()(falsification and bounds) - Sensitivity analysis:
confounding_frontier()(linear-Gaussian confounding frontier) - Survival + competing risks:
causal_spec_survival(),causal_spec_competing()
Example 1: Basic Deficiency Estimation
library(causaldef)
set.seed(42)

# Simulate confounded data (W satisfies back-door criterion)
n <- 500
W <- rnorm(n)
A <- rbinom(n, 1, plogis(0.5 * W))
Y <- 1 + 2 * A + W + rnorm(n)
df <- data.frame(W = W, A = A, Y = Y)

# 1. Define the causal problem
spec <- causal_spec(
  data = df,
  treatment = "A",
  outcome = "Y",
  covariates = "W"
)
#> ✔ Created causal specification: n=500, 1 covariate(s)

# 2. Estimate a deficiency proxy (PS-TV) for different strategies
results <- estimate_deficiency(
  spec,
  methods = c("unadjusted", "iptw", "aipw"),
  n_boot = 100
)
#> ℹ Estimating deficiency: unadjusted
#> ℹ Estimating deficiency: iptw
#> ℹ Estimating deficiency: aipw

print(results)
#>
#> -- Deficiency Proxy Estimates (PS-TV) ------
#>
#>      Method  Delta     SE               CI            Quality
#>  unadjusted 0.1190 0.0230 [0.1048, 0.1982] Insufficient (Red)
#>        iptw 0.0212 0.0099 [0.0142, 0.0537]  Excellent (Green)
#>        aipw 0.0212 0.0087 [0.0154, 0.0483]  Excellent (Green)
#> Note: delta is a propensity-score TV proxy (overlap/balance diagnostic).
#>
#> Best method: aipw (delta = 0.0212 )
Interpretation: Unadjusted $\widehat{\delta} \approx$ 0.119; after IPTW/AIPW, $\widehat{\delta} \approx$ 0.021.
Example 2: Policy Regret Bounds
If we use this evidence to make a policy decision (e.g., approve a drug), what is the worst-case loss?
# Calculate bounds for a utility range of [0, 1]
bounds <- policy_regret_bound(results, utility_range = c(0, 1), method = "aipw")
#> ℹ Transfer penalty: 0.0212 (delta = 0.0212)

print(bounds)
#>
#> -- Policy Regret Bounds -------------------------------------------------
#>
#> * Deficiency delta: 0.0212
#> * Delta mode: point
#> * Delta method: aipw
#> * Delta selection: pre-specified method
#> * Utility range: [0, 1]
#> * Transfer penalty: 0.0212 (additive regret upper bound)
#> * Minimax floor: 0.0106 (worst-case lower bound)
#>
#> Note: this is a plug-in bound using a deficiency proxy rather than an identified exact deficiency.
#>
#> Interpretation: Transfer penalty is 2.1 % of utility range given delta
plot(bounds, type = "safety_curve")
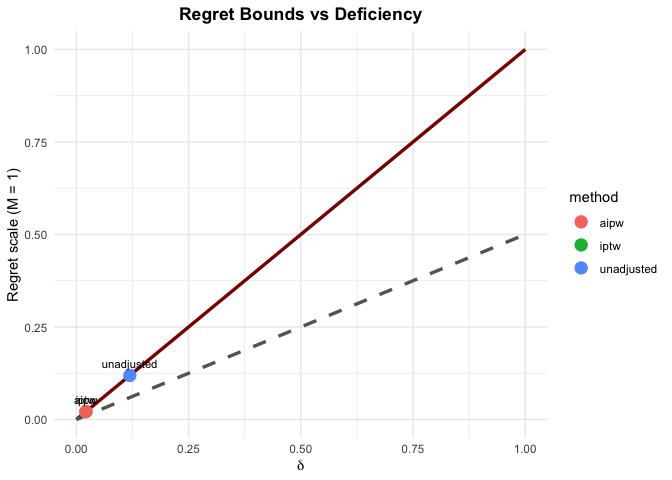
The plug-in transfer penalty is 0.0212 on a 0–1 utility scale; the minimax safety floor is 0.0106.
Example 3: Negative Control Diagnostic
Check if the “Adjusted” strategy actually removes confounding using a negative control outcome $Y_{nc}$ (known to be unaffected by treatment).
# Add a negative control to simulation
df$Y_nc <- W + rnorm(n) # Correlated with W (confounder) but not A

spec_nc <- causal_spec(
  data = df,
  treatment = "A",
  outcome = "Y",
  covariates = "W",
  negative_control = "Y_nc"
)
#> ✔ Created causal specification: n=500, 1 covariate(s)

# Run diagnostic
set.seed(123)
nc_test <- nc_diagnostic(spec_nc, method = "iptw")
#> ℹ Using kappa = 1 (conservative). Consider domain-specific estimation or sensitivity analysis via kappa_range.
#> ✔ No evidence against causal assumptions (p = 0.91045 )
print(nc_test)
#>
#> -- Negative Control Diagnostic ----------------------------------------
#>
#> * screening statistic (weighted corr): 0.0089
#> * delta_NC (association proxy): 0.0089
#> * delta bound (under kappa alignment): 0.0089 (kappa = 1 )
#> * screening p-value: 0.91045
#> * screening method: weighted_permutation_correlation
#>
#> RESULT: NOT REJECTED. This is a screening result, not proof that confounding is absent.
#> NOTE: Your effect estimate must exceed the Noise Floor (delta_bound) to be meaningful.
Here, the screen does not reject (p = 0.91), but that is not proof that confounding is absent; the observable proxy is $\widehat{\delta}_{NC} \approx$ 0.009.
Example 4: Survival Analysis (HCT)
data(hct_outcomes)

# Create an explicit 0/1 event indicator for death
hct <- hct_outcomes
hct$event_death <- as.integer(as.character(hct$event_status) == "Death")

spec_surv <- causal_spec_survival(
  data = hct,
  treatment = "conditioning_intensity",
  time = "time_to_event",
  event = "event_death",
  covariates = c("age", "disease_status", "kps", "donor_type"),
  estimand = "RMST",
  horizon = 24
)
#> ✔ Created survival causal specification: n=800, 131 events

def_surv <- estimate_deficiency(spec_surv, methods = c("unadjusted", "iptw"), n_boot = 50)
#> ℹ Inferred treatment value: Reduced
#> ℹ Estimating deficiency: unadjusted
#> ℹ Estimating deficiency: iptw
print(def_surv)
#>
#> -- Deficiency Proxy Estimates (PS-TV) ------
#>
#>      Method  Delta     SE               CI            Quality
#>  unadjusted 0.3030 0.0460 [0.2505, 0.4189] Insufficient (Red)
#>        iptw 0.0644 0.0219  [0.0498, 0.136]   Caution (Yellow)
#> Note: delta is a propensity-score TV proxy (overlap/balance diagnostic).
#>
#> Best method: iptw (delta = 0.0644 )

bounds_surv <- policy_regret_bound(def_surv, utility_range = c(0, 24), method = "iptw")
#> ℹ Transfer penalty: 1.5457 (delta = 0.0644)
print(bounds_surv)
#>
#> -- Policy Regret Bounds -------------------------------------------------
#>
#> * Deficiency delta: 0.0644
#> * Delta mode: point
#> * Delta method: iptw
#> * Delta selection: pre-specified method
#> * Utility range: [0, 24]
#> * Transfer penalty: 1.5457 (additive regret upper bound)
#> * Minimax floor: 0.7728 (worst-case lower bound)
#>
#> Note: this is a plug-in bound using a deficiency proxy rather than an identified exact deficiency.
#>
#> Interpretation: Transfer penalty is 6.4 % of utility range given delta
In this death-endpoint survival example, IPTW reduces the PS-TV proxy
from about 0.303 to about 0.064, yielding a transfer penalty of about
1.55 months and a minimax floor of about 0.77 months on the 0–24 month
scale. For full relapse-versus-death analyses, use
causal_spec_competing() and estimate_deficiency_competing().
Theory
Based on Akdemir (2026), “Constraints on Causal Inference as Experiment Comparison”.
The core theorem links the deficiency $\delta$ (Total Variation distance) to the max-min regret:
$$ \text{Regret}{do}(\pi) \leq \text{Regret}{obs}(\pi) + M \cdot \delta $$
Where $M$ is the range of the utility function. In practice, the package often provides plug-in bounds by feeding a computable proxy/estimate (e.g., $\widehat{\delta}$) into the regret formula, so the interpretation should track the underlying quantity being supplied.
Citation
@misc{causaldef,
  title = {causaldef: Decision-Theoretic Causal Diagnostics via Experiment Deficiency},
  author = {Akdemir, Deniz},
  year = {2026},
  doi = {10.5281/zenodo.21877511}
}